
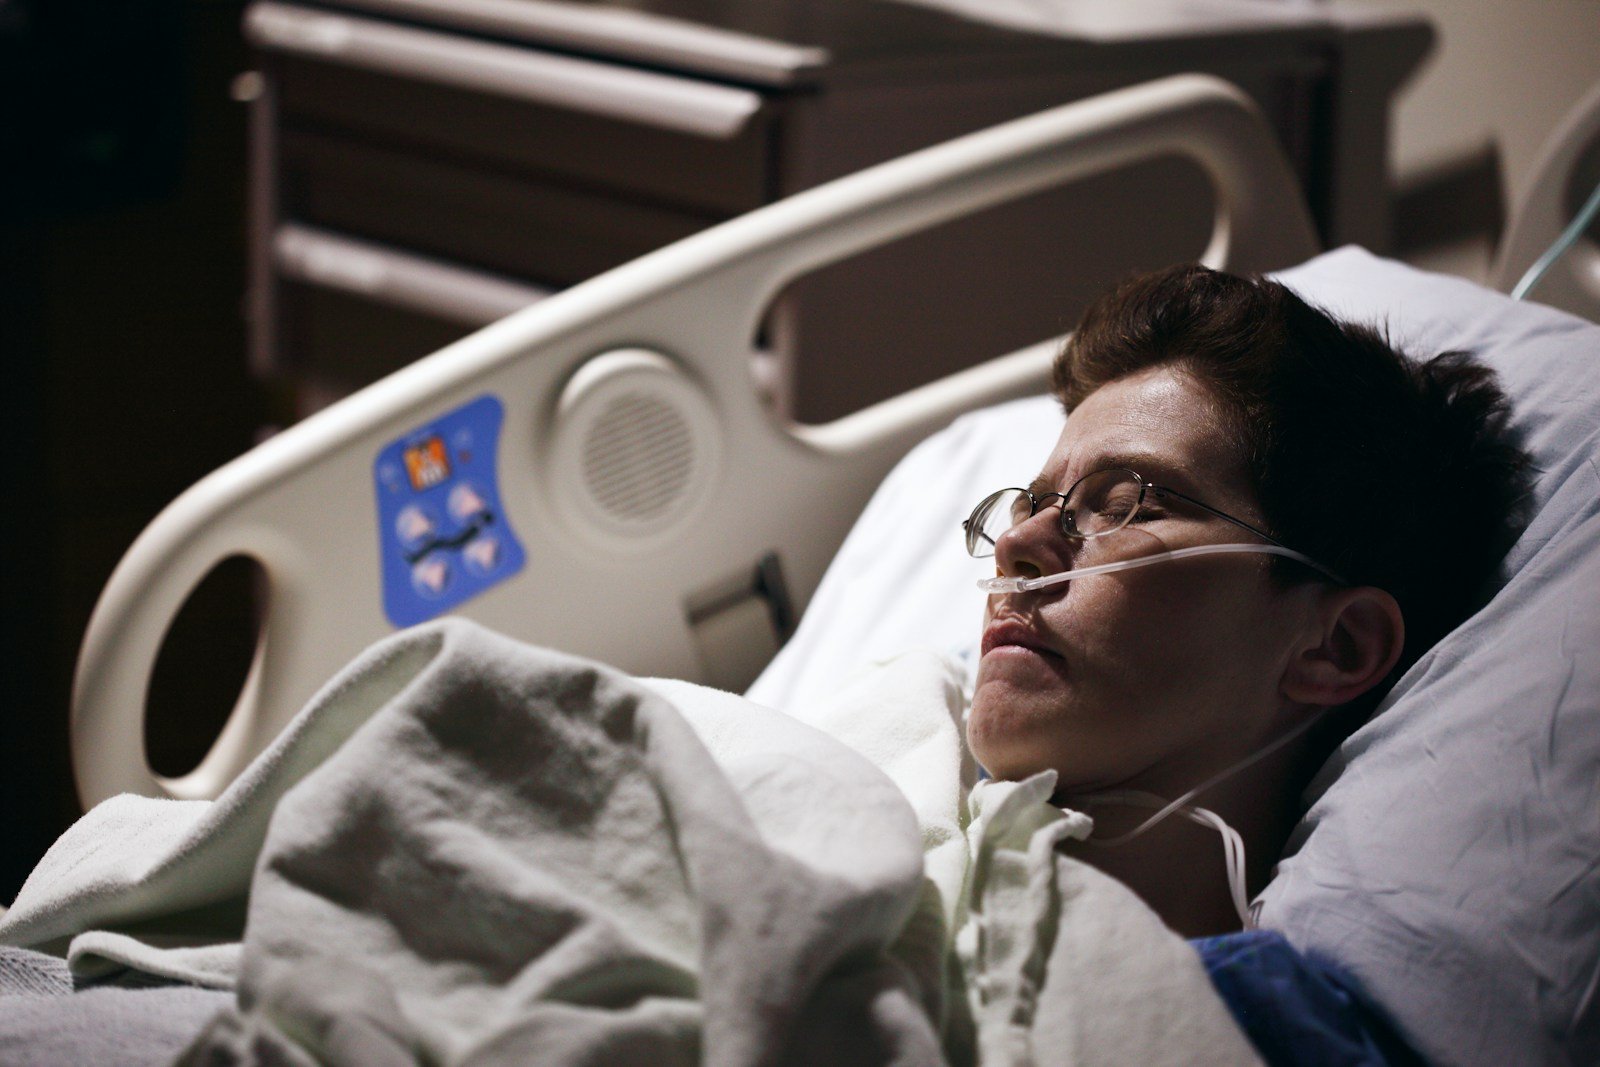
Bed Rails and Restraints in Nursing Homes: Safety Questions
Families sometimes ask a nursing home to “put up the bed rails so Dad cannot fall.”
Bed rails can create their own risks, including entrapment, climbing injuries, and restriction of movement.
Federal nursing-home rules require facilities to try appropriate alternatives before installing a bed or side rail, assess entrapment risk, review risks and benefits, obtain informed consent, and install and maintain the rail correctly.
Bed rails and restraints should not be treated as simple fall-prevention shortcuts.
Federal rules require alternatives first
42 CFR §483.25(n) says a facility must attempt to use appropriate alternatives before installing a side or bed rail.
Ask what problem the team is trying to solve, what alternatives were tried, why they were insufficient, and whether the rail is being proposed for mobility assistance, positioning, or restriction.
The purpose matters.
Entrapment risk must be assessed
Before installation, the facility must assess the resident for risk of entrapment.
Ask whether the assessment considered body size, cognition, mobility, agitation, ability to climb over rails, mattress dimensions, gaps between rail and mattress, and the specific bed-and-rail combination.
Informed consent is required for bed rails
Federal rules require the facility to review risks and benefits with the resident or representative and obtain informed consent before installation.
Ask for that discussion before agreeing.
A restraint is broader than a bed rail
Federal resident-rights rules protect residents from physical or chemical restraints imposed for discipline or convenience and not required to treat medical symptoms.
A device can function as a restraint depending on how it affects the particular resident.
For example, a rail that a mobile resident cannot lower or exit around may restrict freedom of movement.
Ask the clinical team how the device is classified for this resident.
Fall prevention should be individualized
Safer alternatives may include a lower bed, floor mat, better lighting, toileting plan, medication review, closer supervision, transfer assistance, therapy, mobility equipment, or room arrangement.
The right approach depends on the fall pattern.
Ask how the rail is maintained
Federal rules also require correct installation, use, maintenance, and appropriate bed dimensions.
Ask who inspects the rail, how often, whether the mattress is compatible, whether the rail has loosened, and what happens after equipment replacement.
Test the nighttime and self-mobility scenario
Ask what the resident actually does when trying to turn, sit up, reach the bathroom, or get out of bed at night. A rail that seems helpful during repositioning can create a different problem if the resident attempts to climb over, squeeze around, or becomes confused by it.
The bed-rail decision should sit inside the resident’s broader fall-prevention plan. Use the senior-living fall-prevention checklist to ask about toileting, lighting, footwear, medications, mobility aids, supervision, and other alternatives.
A practical example
A family requests full-length bed rails because their mother has fallen twice.
The clinical team finds that she climbs over the rail when confused at night, increasing injury risk.
The team uses a lower bed, scheduled toileting, better lighting, and closer nighttime supervision instead.
The family’s goal — preventing injury — remains the same even though the chosen intervention changes.
Seven questions before agreeing to bed rails
- What specific problem is the rail intended to solve?
- What alternatives were tried?
- Was entrapment risk assessed?
- What risks and benefits were explained?
- Could the rail function as a restraint for this resident?
- How is the rail installed and maintained?
- How will the need be reassessed?
See After a Fall in a Nursing Home.
Sources and review date
Sources checked October 12, 2026.





